Democratic Republic of Congo: Children disproportionately affected, yet left behind in Ebola disease outbreak
Young Ebola disease patients face higher risks, limited care and delayed access to innovations.
Children are paying a devastating price in the Ebola disease outbreak unfolding in northeastern Democratic Republic of Congo (DRC). While children face a higher risk of death from Ebola disease than adults, they also represent a significant proportion of those affected by the current outbreak. According to Epicentre, the epidemiological research centre of Doctors Without Borders/Médecins Sans Frontières (MSF), nearly one in four confirmed Ebola disease cases in North Kivu is a child. MSF is deeply concerned by the disproportionate impact of the disease on children and calls for more attention to their specific vulnerabilities in both the medical and research response.
“On top of enormous challenges caring for young patients, medical facilities are dealing with a lack of pediatric dosing guidance and limited availability of child-friendly formulations of investigational medicines.”
Guyguy Manangama, epidemiologist and deputy director of operations at MSF
While Ebola remains a deadly disease for all age groups, the youngest children face the highest risk of death. In North Kivu, children have been particularly affected by the current outbreak: 24 per cent of confirmed cases are among children under five years of age, compared with 13 per cent in Ituri, while infants under one-year-old account for 13 per cent of cases, compared with six per cent in Ituri. At the Ebola treatment centre (ETC) in Butembo, North Kivu, MSF teams have observed the case fatality rate among children as particularly high. Between June and September 2026, 24 out of 30 children — most of whom are under the age of five — died from the Bundibugyo virus in this ETC alone. The rapid progression of the disease in communities and limited access to specialized care at the health facility level are contributing to such alarmingly high fatality rates.
Providing comfort to children in Ebola treatment centres
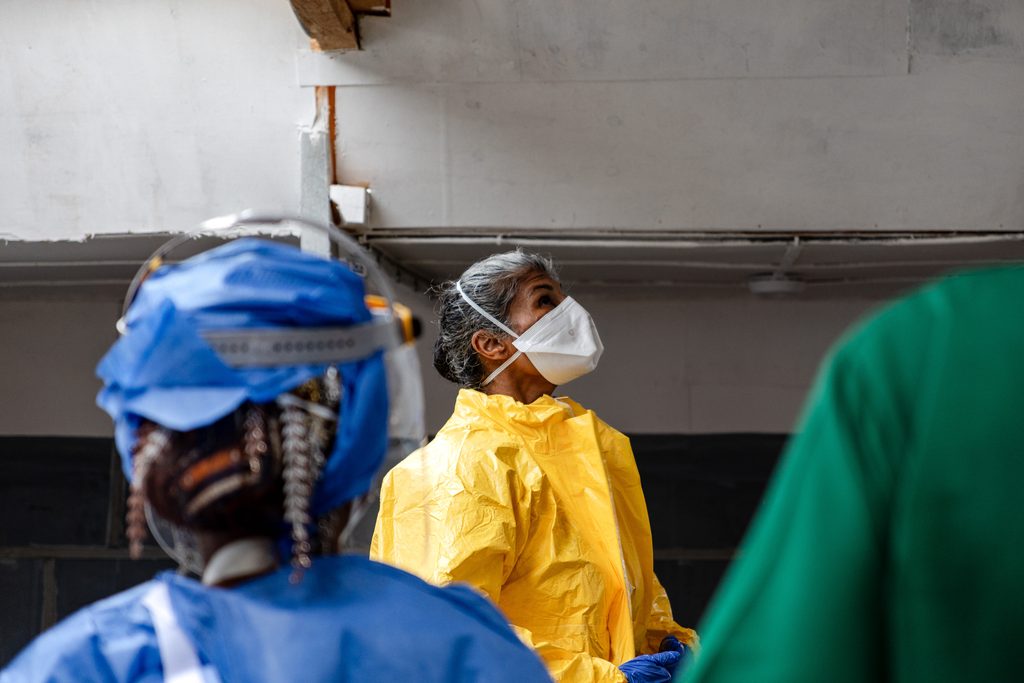
Efforts have been made to reduce the emotional toll of isolation on children in ETCs, including the creation of visibility areas where parents can see and communicate with their hospitalized children. However, being admitted to an ETC remains a deeply distressing experience for young patients. Children may be too young to understand their situation or meet their own basic needs. To help address this situation, MSF has recruited and trained caregivers who provide daily support and comfort to children inside several MSF-supported ETCs while wearing full personal protective equipment. These caregivers come from diverse backgrounds, including but not limited to Ebola survivors. At Kitatumba Ebola treatment centre in Butembo, 13 caregivers are supporting children. While far from a perfect solution, this initiative provides essential human contact and emotional support for children facing the outbreak.
“On top of enormous challenges caring for young patients, medical facilities are dealing with a lack of pediatric dosing guidance and limited availability of child-friendly formulations of investigational medicines,” says Guyguy Manangama, epidemiologist and deputy director of operations at MSF. “A child-centred approach must be at the heart of medical care, operational planning and research efforts.”

Children left behind in Ebola research and treatment
Children have been disproportionately affected by the current outbreak, yet they are left behind when it comes to access to innovative medical tools. Historically, children are often excluded from clinical research or included only after significant delays, creating dangerous gaps in evidence and access to potentially lifesaving interventions.
“Treatments, vaccines and other preventive tools should be evaluated for use in children from the outset of research efforts and made available to them without delay,” says Manangama. “Yet in the current outbreak, children are still being left behind, with very limited access to vaccination trials and campaigns, as well as the latest therapeutic innovations despite bearing a significant burden of disease. Children cannot continue to wait for data generated in adults before benefiting from advances in Ebola care and prevention.”
MSF urges national authorities, research institutions, pharmaceutical developers and international funders to prioritize the inclusion of children in all ongoing and future Bundibugyo virus studies. Ensuring equitable access to research and new medical tools, including vaccines, is essential to reducing preventable deaths and improving outcomes for one of the most at-risk groups.
The impact of the outbreak on children extends beyond Ebola disease infection itself. Disruptions to essential health services can rapidly increase risks from vaccine-preventable diseases, malnutrition and other common childhood illnesses. Preserving routine immunization, nutrition programs and access to primary healthcare must therefore be considered a core component of the outbreak response, not an afterthought.
Potential treatment
One ongoing study, EBO-PEP, is evaluating an oral antiviral drug, obeldesivir, to prevent Ebola infection after high-risk exposure. If proven effective, the treatment could provide a practical way to protect people who have recently been in contact with an Ebola patient. While the trial is expected to expand eligibility to include some children, those under 20 kilograms remain excluded because an appropriate pediatric formulation is not yet available.
For the youngest children, the current alternative involves a 10-day course of intravenous treatment, an approach that is particularly difficult to implement in outbreak settings and can be especially challenging for young patients and their caregivers. More information here: An urgent opportunity to ensure children’s access to oral post-exposure prophylaxis trials for Bundibugyo virus disease – The Lancet Child & Adolescent Health
Vaccination
While the results of ongoing trials evaluating vaccines specifically designed for the Bundibugyo virus are not expected for several months, ERVEBO® is an immediately available option. Its safety profile is well established, it is approved for use in children aged one year and older and health authorities in DRC have extensive experience using it in outbreak settings. Emerging evidence also suggests it may offer some protection against the Bundibugyo virus, although the degree of protection needs to be clarified. In areas at high risk of Ebola disease transmission, vaccinating contacts of confirmed cases, including children over one year of age, could help prevent severe illness and save lives.