Ebola emergency
The current Ebola disease outbreak is a crisis within a crisis as it is unfolding in regions already affected by decades of conflict, displacement, violence and an extremely weak health system, with millions of people in need of humanitarian assistance. This outbreak has become the largest and deadliest in Democratic Republic of Congo (DRC) and it continues to spread at an alarming rate.
MSF staff are leading experts in treating and containing Ebola disease. Our teams worked tirelessly throughout the massive 2014 to 2016 West Africa epidemic and have responded to multiple outbreaks in DRC alone.
DRC is facing the worst Ebola outbreak in its history, with the fastest spread ever recorded. During the first 100 days of the outbreak, DRC recorded nearly six times as many infections as were reported during the early stages of the 2014–16 West Africa epidemic — the deadliest on record.
As of Oct. 28, there have been more than 10,000 confirmed cases and over 4,900 reported deaths The true scale of the outbreak is likely even greater, as surveillance gaps and limited access to some affected areas mean that not all cases are detected or reported.
Seventy-six per cent of all confirmed cases have been recorded in Ituri province, the outbreak’s original epicentre. However, North Kivu now accounts for nearly half of all newly reported cases and is recording the highest case fatality rate in the country, at 59 per cent.
Meanwhile, the confirmation of two cases in South Ubangi has expanded the outbreak’s geographic footprint to seven provinces. Nationally, the number of new cases has not fallen. The outbreak is not shrinking; it is moving into new, underprepared areas, making containment efforts increasingly challenging. Approximately two-thirds (66 per cent) of confirmed deaths occur in the community.
Ebola disease is not just confined to DRC. An outbreak that began in Uganda in May, ended in August. More recently, cases have been reported in Kenya and Nigeria.
Clinical trials of treatments and vaccines
Unlike most previous Ebola disease outbreaks, the current outbreak is caused by the Bundibugyo virus. Ebola disease caused by the Bundibugyo virus kills up to 40 per cent of people infected, which is less lethal than the more common Ebola disease virus
There is currently no licensed and available vaccine specifically for Bundibugyo Ebola virus disease. However, a vaccination campaign is ongoing for frontline workers in Ituri and North Kivu with the ERVEBO vaccine, which was developed for Zaire ebolavirus, not Bundibugyo ebolavirus. The level of protection for humans, if any, remains unknown, but it may offer some cross-protection against Bundibugyo Ebola, but this has not yet been proven. Vaccination is voluntary and does not replace other measures needed to end the outbreak.
MSF has launched the BRAVO study to document and evaluate the use of the ERVEBO vaccine among frontline workers during the current Bundibugyo Ebola outbreak. It is being conducted in collaboration with DRC’s Ministry of Health, the Congolese National Institute for Biomedical Research (INRB), Africa CDC, Epicentre (epidemiological research branch of MSF), and research partners. It will run for a period of nine to twelve months, including three months dedicated to vaccination and a minimum of six months of participant follow-up. It has a target population of 20,000 frontline workers. Between Sept. 19–29, more than 750 frontline workers were vaccinated in Bunia.
Additionally, MSF, along with other medical organisations involved in the outbreak response, is actively supporting the scientific PARTNERS clinical trial. This study will help identify the most effective type of treatment for patients affected by Bundibugyo virus disease. During the previous Ebola disease outbreak in the DRC, similar treatment trials proved instrumental in identifying effective treatments for Ebola virus disease (EVD).
As the current Ebola disease outbreak disproportionately affects children, they can’t be left out from any research taking place on Ebola disease. MSF also calls for urgent action from all stakeholders involved in Bundibugyo virus treatment and prevention research to ensure that children are meaningfully included in planned, evidence-generating research on medical countermeasures, and, in particular, have timely access to pediatric formulations for ongoing trials of oral post-exposure prophylaxis (PEP).
HOW CAN I HELP MSF?
Right now, our teams are responding in DRC. Donate now to help MSF medical teams act fast and support people facing emergencies around the world.


The latest: How is MSF responding to the Ebola disease outbreak?
MSF is supporting the response in five of the seven affected provinces: Ituri, North Kivu, Tshopo, Haut-Uélé and Sud Ubangi.
Key figures for May 15, 2026 – Sept. 27, 2026. MSF:
- Supported the Ebola disease outbreak response in DRC with 2,800 staff. The vast majority are locally hired
- Is running eight Ebola Treatment Centres and numerous Isolation units. The current capacity is around 300 beds
- Has admitted more than 3,500 patients
- Has confirmed 1,600 Ebola disease-cases
- Seen more than 580 people cured.
Beyond patient care and treatment, MSF is actively working across other important response pillars helping to limit transmission, strengthen local capacity, and improve access to care.
It is important to note that the Ebola disease outbreak is not the only health emergency that communities are facing in DRC. Essential services such as vaccination, maternal health, sexual and reproductive healthcare, nutrition, care for survivors of sexual violence, treatment for infectious diseases and other urgent medical needs must also continue.
MSF teams are often among the first humanitarian responders for one key reason: because we are already there. MSF has been working in DRC since 1977, providing vital healthcare services through conflict, disaster and disease.

- More than 600 MSF staff are directly responding to the Ebola disease outbreak in DRC, working alongside Ministry of Health (MoH) teams. They are supported by more than 2,700 MSF staff, and nearly 4,500 incentivized MoH staff already working in the country on existing health programs, helping ensure that other essential health services continue. In Uganda, MSF has 20 staff responding to the outbreak. The response, led by the Congolese Ministry of Health and supported by several international partners, is expanding but still falls short of what is needed as the outbreak keeps spreading to new areas
- The outbreak is currently centred in Ituri, with the main epicentre around Bunia, Mongbwalu, Rwampara and Nyankunde health zones. However, other areas – outside of urban ones – show either none or little support by humanitarian actors
- Despite the recent scale up in efforts, MSF is still seeing critical gaps in response capacity, including in surveillance, testing, community engagement and rapid case detection
- MSF staff with experience responding to Ebola disease outbreaks continue being sent to DRC to as part of the emergency response. They will provide support to existing medical projects and respond to new alerts in surrounding areas
- MSF works to ensure strict infection prevention measures are in place for healthcare projects and facilities in DRC. We must protect patients and staff and ensure they can continue to access medical services
- MSF’s Ebola response is based on six pillars: caring for and isolating patients; tracing and follow-up of patient contacts; raising community awareness of the disease (such as how to prevent it and where to seek care); conducting safe burials; proactively detecting new cases; and supporting existing health facilities.

What is Ebola disease?
Ebola is a rare but deadly disease which can kill up to 90 per cent of those infected.
The most commonly known viruses within the Ebola disease genus are the Ebola virus, the Sudan virus and the Bundibugyo virus. There is an approved treatment and a preventive vaccine for the Ebola virus. But the current Ebola disease outbreak reported in DRC is caused by the Bundibugyo virus, for which there is no approved vaccine or treatment.
It can be difficult to diagnose because the early symptoms, like a fever and sore throat, are common. To confirm an Ebola disease diagnosis, special tests need to be carried out. These require test kits specific not to the disease itself, but to each individual virus in order to detect it. However, these test kits are currently in short supply for the Bundibugyo virus, which significantly slows down case confirmation and, consequently, the implementation of contact tracing and patient isolation.
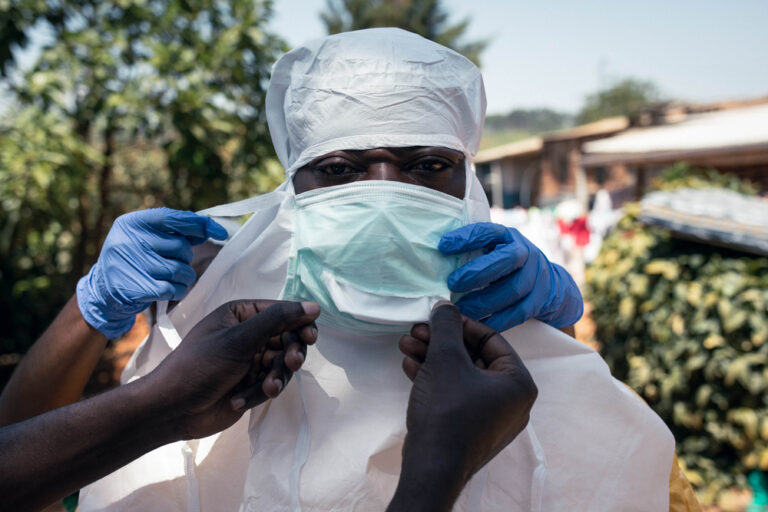
Ebola disease is highly infectious and can be transmitted from both animals and humans. Human-to-human transmission happens through close contact with blood, secretions or other bodily fluids of infected individuals. This is why people have to wear full personal protective equipment to prevent catching or spreading the virus.
Medical teams can give patients the best chance of survival by helping to manage the symptoms of the virus and treating other diseases the patient may have.
Once a patient recovers from Ebola disease, they’re immune to the form of the virus they contracted.

MSF’S response to Ebola in the West Africa
Between late 2013 and 2016, an outbreak of Ebola in West Africa became a major international emergency. The severity of the epidemic saw MSF launch one of the largest emergency operations in our history.
MSF responded in the three most affected countries — Guinea, Sierra Leone and Liberia — and also to the spread of cases to Nigeria, Senegal and Mali.
At the peak of the epidemic, MSF employed nearly 4,000 local medical staff and more than 325 international staff who ran Ebola treatment centres, as well as conducted surveillance, contact tracing, health promotion and provided psychological support.
MSF admitted 10,310 patients to our Ebola management centres, of which 5,201 were confirmed Ebola cases, representing one-third of all WHO-confirmed cases.
Myths & Truths About Ebola Disease (Bundibugyo virus)
| Myth | Truth |
| There is no point going to a treatment centre if there is no specific cure. | Even though there is currently no approved vaccine or specific treatment for Ebola caused by the Bundibugyo virus, treatment centres provide essential supportive care. This includes fluids, oxygen, nutrition and symptoms relief such as fever, vomiting, diarrhea and pain. This care helps the body fight the infection and improves the chances of survival. |
| If I am isolated, it means I already have Ebola disease. | Isolation is not a confirmation of disease. It is a precautionary step while tests are being done, because early symptoms of Ebola disease can look like other illnesses such as malaria or typhoid. Once results are available, isolation can be adapted depending on the diagnosis. |
| I only have mild symptoms, so I don’t need to go to a treatment centre. | Common symptoms like fever, headache, vomiting or diarrhea can mimic malaria, flu or typhoid. During an Ebola outbreak, it’s important to isolate and get tested to rule out Ebola disease, even if the chance is low. Early assessment and temporary isolation help protect you, your family, healthcare workers and the community. Getting checked early is always the safest choice. |
| If I am in a treatment centre, I cannot see or speak to my family. | Treatment centres are organized to maintain safe communication between patients and families. Whenever possible, patients can communicate through safe visiting areas or other communication tools. Maintaining family connection is part of overall care and wellbeing. |
| Doctors will use experimental drugs on patients without consent. | Although clinical trials began in early July, they are strictly regulated. These trials have been approved by international medical and ethical authorities and are conducted in close collaboration with health authorities. Participation in these trials remains strictly free and voluntary. Each patient receives clear explanations before making a decision. Refusing to participate would in no way affect access to standard medical care. |
| Ebola disease outbreaks are used for business or profit. | Ebola disease is a rare and highly dangerous illness that requires a fast and large-scale medical response to save lives and prevent further transmission. Because of this urgency, international health institutions mobilize quickly. This is not driven by profit, but by the need to respond effectively to a serious public health emergency. MSF uses our funding exclusively for medical and humanitarian activities – during Ebola outbreaks and beyond – including providing care for other essential health needs such as malaria, maternal health and pediatric services. |